Onir Resources
The Drug That Helps You Quit or Cut Back on Alcohol October 2026
Discover prescription options like naltrexone that help you drink less, plus how Onir makes getting a prescription simple this October. October 2026

By Justine Fowey, Onir Health Editorial Team
· Updated

If this describes your evenings, a licensed clinician can review the rest privately. Takes 60 seconds.
Somewhere between 'I should drink less' and actually drinking less, most people get stuck. Not because they lack motivation, but because willpower alone is working against how alcohol actually affects the brain. There are prescription medications built exactly for that gap, and they're more accessible than most people realize.
TLDR:
- Three FDA-approved drugs can help you drink less or quit: naltrexone, acamprosate, and disulfiram.
- Fewer than 10% of people with alcohol use disorder receive any treatment, often because they don't know medication exists.
- Naltrexone blocks the brain's reward signal from drinking and can be prescribed by any primary care doctor or via telehealth.
- No drug to stop drinking is available over the counter in the US; supplements don't come close to what prescriptions do.
- Onir handles naltrexone intake, clinician review, and mail delivery online, with no insurance claim filed.
What Is Alcohol Use Disorder, and Who Is a Candidate for Medication?
Alcohol use disorder is a clinical diagnosis, but the range of people it describes is wider than most realize. At the mild end, it might look like a few too many drinks most nights, a growing reliance on alcohol to unwind, or a pattern you keep meaning to change. At the severe end, it involves physical dependence and withdrawal. All of it counts.
According to the NIAAA, approximately 28 million Americans aged 12 and older live with AUD, spanning weekend binge drinkers and daily drinkers alike. You do not need to have lost everything, or even identify with the word "alcoholic," to qualify for medical treatment.
Medication is a legitimate, guideline-supported option for mild, moderate, and severe AUD. The same way a physician might prescribe something for high blood pressure without waiting for a heart attack, prescribing for AUD does not require hitting rock bottom first.
Why So Few People Use Medication to Stop Drinking
The medications exist. They're FDA-approved, widely studied, and prescribed by regular primary care doctors. Yet fewer than 10% of people with a past-year alcohol use disorder receive any treatment at all, and medication in particular is even rarer.
A few reasons for that gap:
- Most people assume treatment means inpatient rehab or AA, not a prescription
- Stigma keeps people from bringing it up with their doctor
- Many physicians don't routinely screen for or offer medication
- Most patients simply don't know these drugs exist
A large share of people searching "is there a drug to stop drinking alcohol" are genuinely surprised the answer is yes, and has been for decades.
How Prescription Drugs for Alcohol Work in the Brain
Alcohol is habit-forming partly because of what it does in the brain. When you drink, your brain releases endorphins, which bind to opioid receptors and generate a reward signal. Over time, that signal becomes the engine behind habitual drinking.
Prescription medications interrupt this cycle in different ways. A Swedish cohort study of 125,556 people with AUD found that those taking approved medications had substantially lower rates of hospitalization and death compared to those who received no medication.
Medication | FDA-Approved | Best For | How It Works | Key Consideration |
|---|---|---|---|---|
Naltrexone | Yes (1994) | Cutting back or quitting | Blocks opioid receptors; blunts alcohol's reward signal | Cannot be used within 7 to 10 days of opioid use |
Acamprosate (Campral) | Yes | Staying sober after quitting | Stabilizes glutamate/GABA balance; reduces post-quit anxiety and cravings | Must start after detox; requires functioning kidneys |
Disulfiram (Antabuse) | Yes | Hard deterrent for motivated quitters | Blocks acetaldehyde breakdown; makes drinking physically unpleasant | Only works if taken consistently; multiple drug interactions |
Topiramate | No (off-label) | Reducing heavy drinking days | Dampens glutamate, boosts GABA; reduces cravings | Harder side effect profile (cognitive slowing, word-finding difficulty) |
Gabapentin | No (off-label) | Post-quit sleep and anxiety | Eases withdrawal-related anxiety and sleep disruption | Misuse potential; prescribers tend to be selective |
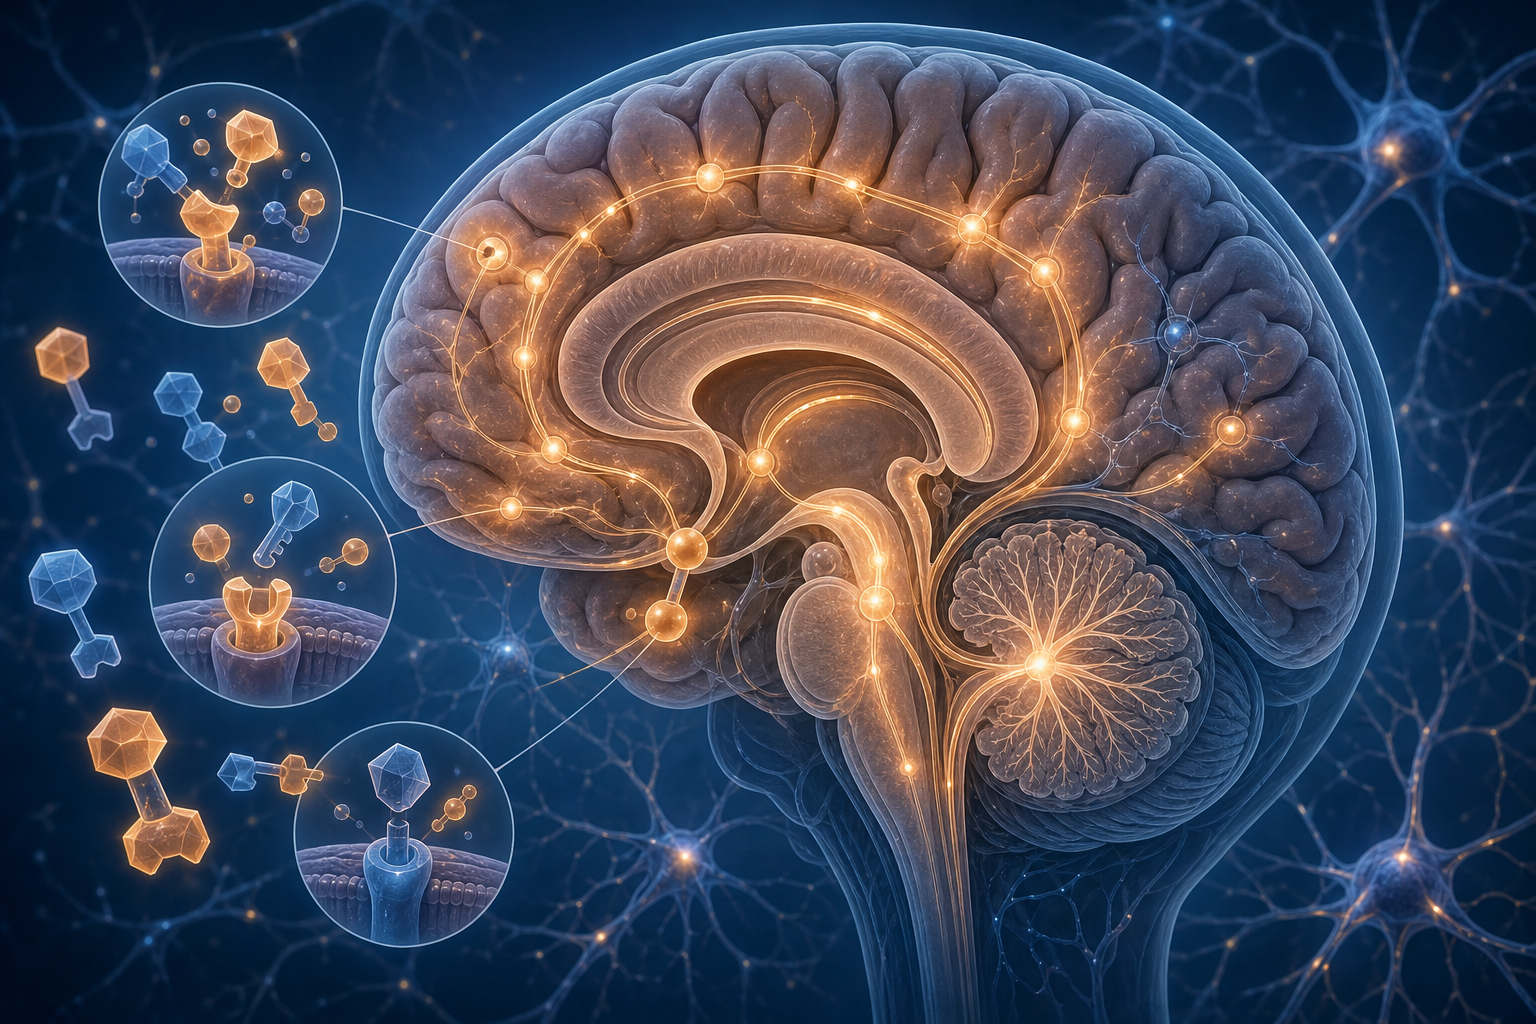
- Some block opioid receptors so the reward signal never registers, making drinking feel less worth it.
- Others quiet the anxiety and cravings that surface after you quit by working on different neurotransmitter systems.
None of these drugs are addictive or habit-forming. They work on the mechanism of drinking, not by substituting one dependency for another.
Naltrexone: The Most Commonly Prescribed Drug to Stop Drinking
Naltrexone is FDA-approved for alcohol use disorder and has been in use since 1994. It's a generic medication prescribed by primary care doctors, psychiatrists, and telehealth clinicians alike.
It blocks opioid receptors, so when you drink, the endorphin reward signal doesn't land the same way. The buzz is blunted. Over time, naltrexone helps you drink less as the brain starts to unlearn the link between drinking and pleasure, and cravings tend to follow.
Two main forms are available:
- Oral tablet (50 mg), taken daily or as needed before drinking, offering flexibility in how you use it
- Injectable form (Vivitrol), a monthly 380 mg shot given at a clinic, which suits people who prefer not to manage a daily pill
Naltrexone side effects are generally mild and fade within the first week or two: nausea, fatigue, headache, reduced appetite. Taking the tablet with food helps.
One hard safety rule: do not take naltrexone if you have used any opioid, including heroin, fentanyl, or oxycodone, in the past 7 to 10 days. If opioids are part of the picture, careful medical clearance comes first.
The Sinclair Method: Taking Naltrexone Only Before You Drink
Developed by Dr. John D. Sinclair, the Sinclair Method is built around pharmacological extinction: timing your naltrexone dose means taking it one hour before drinking, and only then. Each time you drink with opioid receptors blocked, the brain gets no reward. Repeated over weeks and months, the association between drinking and pleasure gradually fades.
The practical appeal is real. You continue drinking at the start of treatment, and most people find they want to drink less without forcing willpower into the equation. For people whose goal is to drink less without quitting completely and not quit outright, this fits more naturally than abstinence-first approaches.

Research on the Sinclair Method confirms that naltrexone used this way is FDA-approved for alcohol dependence, well tolerated, and not habit-forming.
Acamprosate: The Drug for People Who Have Already Quit
Acamprosate (brand name Campral) is FDA-approved for alcohol use disorder, but its role is specific: it helps people who have already stopped drinking stay stopped.
Where naltrexone targets the reward system, acamprosate works on glutamate and GABA neurotransmitter systems. Quitting alcohol disrupts this balance, and the resulting anxiety, restlessness, and low-level discomfort can persist for weeks or months after detox. Acamprosate helps stabilize that, reducing the chronic unease that often drives relapse.
A few things to know about how it's used:
- It starts after detox, not during active drinking, which raises a different question than how long to take naltrexone for reward-based drinking
- Typical dosing is two 333 mg tablets taken three times daily
- Side effects are mostly gastrointestinal and tend to ease over time
- It does not affect liver metabolism, making it an option when liver concerns rule out other medications
If want to drink less without quitting, acamprosate is not the right fit. It is designed for people committed to full abstinence who need support during a longer withdrawal window than most people expect.
Disulfiram: The Deterrent Drug That Makes Drinking Unpleasant
Disulfiram (brand name Antabuse) takes a fundamentally different approach. Instead of softening the reward of drinking, it makes drinking unpleasant enough that most people simply stop.
The mechanism is straightforward: disulfiram blocks the enzyme that breaks down acetaldehyde, a toxic byproduct of alcohol metabolism. If you drink while it's in your system, acetaldehyde builds up quickly, causing flushing, nausea, vomiting, and a rapid heartbeat within minutes, sometimes lasting hours.
Clinicians generally reach for naltrexone or acamprosate first, and consider disulfiram when those haven't worked or when someone wants a hard behavioral deterrent. It works best for people who are highly motivated and want something that removes the choice entirely.
The catch is obvious: it only works if you take it. Someone who decides to drink can simply stop and wait a few days for it to clear. Even without alcohol, disulfiram can cause fatigue, mild drowsiness, or a metallic aftertaste, and it interacts with some common medications, so a full medication review before starting is necessary.
Off-Label Options: Topiramate and Gabapentin
Neither topiramate nor gabapentin carries an FDA approval for alcohol use disorder, but both are prescribed for it regularly. "Off-label" simply means a drug approved for one condition is used by clinicians for another based on available evidence. This is common practice in medicine and does not mean experimental or unsafe.
Topiramate is an anticonvulsant with a reasonable body of clinical evidence showing it can reduce heavy drinking days and cravings, partly by dampening glutamate activity and boosting GABA. The tradeoff is a harder side effect profile: cognitive slowing, word-finding difficulty, and tingling in the hands and feet are fairly common at higher doses.
Gabapentin is sometimes used in the post-quit window, when sleep disruption and anxiety can make staying off alcohol difficult. Side effects include drowsiness and dizziness, and there are concerns about misuse potential in people with certain histories, so prescribers tend to be selective.
Both require a physician familiar with AUD treatment and are worth asking about if first-line medications have not worked for you.
Is There a Drug to Stop Drinking Over the Counter?
No FDA-approved medication for alcohol use disorder is available over the counter in the United States. Naltrexone, acamprosate, and disulfiram all require a prescription, and there is no OTC equivalent.
Some supplements come up in recovery circles: magnesium, B vitamins (thiamine in particular), and NAC are commonly discussed. Thiamine matters because heavy drinking depletes it. But none of these reduce cravings, block alcohol's reward signal, or treat AUD the way prescription medications do. The clinical evidence for that level of effect simply is not there.
If you want something that genuinely changes your relationship with alcohol, the prescription route is the one with research behind it.
How to Talk to a Doctor About Getting a Prescription
You do not need a specialist referral. Any licensed primary care doctor or psychiatrist can prescribe naltrexone, acamprosate, or disulfiram. The barrier is usually the conversation, not the credential.
Most people hesitate because they worry about being judged or lectured, which is part of why some look for private help to drink less instead. A good physician will ask practical questions: how much you drink, how often, what medications you take, and whether opioids are part of the picture. That last one matters because of the safety interaction with naltrexone. Bring a rough sense of your drinking history and a list of current medications, and the appointment moves quickly.
Telehealth has made this considerably easier. You can now get a naltrexone prescription through an online intake without an in-person visit, with some providers turning around a prescription in as little as 24 to 48 hours, though timelines vary widely by service. (Onir's own clinician review is typically within 24 hours, with medication in hand in 5 to 7 business days.)
Who Should Not Take These Medications
Each of these medications has specific contraindications worth knowing before you pursue a prescription.
- Naltrexone: off-limits if you have used any opioid in the past 7 to 10 days. Naltrexone and liver safety is a caution, not an automatic disqualifier, but a physician needs to assess severity first.
- Acamprosate: requires reasonably functioning kidneys, since it is cleared renally. Serious kidney impairment rules it out.
- Disulfiram: interacts with more substances than most people expect, including certain antibiotics, cough syrups containing alcohol, and some topical products. A full medication review before starting is necessary.
Heavy daily drinkers face a separate concern: stopping abruptly can trigger alcohol withdrawal, which in severe cases involves seizures. That is not a reason to avoid medication, but it may mean medical supervision during detox needs to come first. A clinician will ask the right questions to figure out whether that applies to you.
None of this is meant to discourage you. It explains why a clinical evaluation is part of the process, not a bureaucratic hoop.
How Onir Makes the Naltrexone Prescription Process Accessible
Onir handles the full naltrexone care journey online, from intake to delivery. Getting started takes about 15 to 20 minutes: you fill out a medical intake form covering your drinking history, current medications, and health background. A licensed clinician reviews it and responds via secure, asynchronous text-based chat, typically within 24 hours. If naltrexone is appropriate, the prescription goes to the pharmacy the same day in most cases.
Medication ships through InnovaScript, a mail-order pharmacy licensed in all 50 states, arriving in plain, unmarked packaging, after you complete the free assessment. Total time from intake to medication in hand is typically 5 to 7 business days. Onir prescribes FDA-approved generic naltrexone hydrochloride 50 mg tablets.
The service is self-pay, so no insurance claim is filed and there is no paper trail. See how much Onir costs for details. Records are protected under HIPAA and 42 CFR Part 2, which gives substance use treatment records some of the strongest federal privacy protections that exist. Onir will not contact your primary care doctor unless you ask.
If your drinking has become automatic but you have no interest in rehab or group meetings, this is a quieter path to the same medication your doctor could prescribe in person.
Final Thoughts on Drugs That Stop Drinking and How to Access Them
Naltrexone has been FDA-approved since 1994, yet medication for AUD stays surprisingly under the radar. Most people find the conversation with a doctor far less difficult than they expected, and telehealth has made that conversation easier to have privately. Whatever your goal with alcohol, there's a prescription option designed to support it.
FAQ
What is the prescription drug that helps you stop drinking, and how does it work?
Naltrexone is the most commonly prescribed drug to help stop or cut back on drinking. It blocks the opioid receptors that carry alcohol's reward signal, so the buzz feels blunted and the brain gradually unlearns the habit of reaching for a drink. It has been FDA-approved for alcohol use disorder since 1994, is non-addictive, and is available as a daily tablet or a monthly injectable called Vivitrol.
Is there a drug to stop drinking available over the counter?
No. Naltrexone, acamprosate (Campral), and disulfiram (Antabuse) all require a prescription in the United States, and there is no OTC equivalent that works the same way. Supplements like B vitamins and magnesium are worth taking if you drink heavily, since alcohol depletes them, but none reduce cravings or block alcohol's reward signal the way prescription medications do.
Oar Health vs Ria Health vs Onir for getting a naltrexone prescription online?
All three are telehealth services that prescribe naltrexone for alcohol use disorder, but they differ in structure and positioning. Oar Health and Ria Health both offer coaching layers and, in some cases, insurance billing pathways; Onir is fully self-pay, ships medication in plain unmarked packaging, and files no insurance claim, which appeals to people who want no paper trail connecting their name to AUD treatment. If privacy from employers or a primary care doctor is a real concern for you, Onir's self-pay model is worth weighing directly against the others.
Can I cut back on drinking without quitting completely, and will a doctor still prescribe medication?
Yes on both counts. Naltrexone is used by many people whose goal is to drink less on weeknights or reduce heavy episodes, not to stop entirely. See the Sinclair Method section above for how dose timing works. Clinicians who prescribe for alcohol use disorder generally build the plan around your goal, whether that is moderation or full abstinence.
When should I stop drinking before starting naltrexone, and are there safety rules I need to know?
Alcohol is not the safety concern with naltrexone; opioids are. You must be free of all opioids, including heroin, fentanyl, and oxycodone, for at least 7 to 10 days before your first dose, or you risk immediate withdrawal. If you are a heavy daily drinker, stopping abruptly before starting any medication can also carry its own medical risks, so a clinician will ask about your drinking pattern during intake to determine whether supervised detox should come first.
The science behind Onir has been covered by
82%
drinking less within two weeks
30+ yrs
FDA-approved & clinically studied
1,200+
clinical studies behind it
$99
per month, shipped discreetly
In their words
“I set one alarm for 5 p.m. and stopped thinking about it. Three weeks later the second glass just wasn't interesting anymore. No willpower involved.”
Individual results vary.
A quieter next step, when you want one
If practical changes have not been enough, a licensed clinician can review the rest privately. It doesn't commit you to anything.
60 seconds · 11 questions · Fully refunded if you're not approved